

ABSTRACT
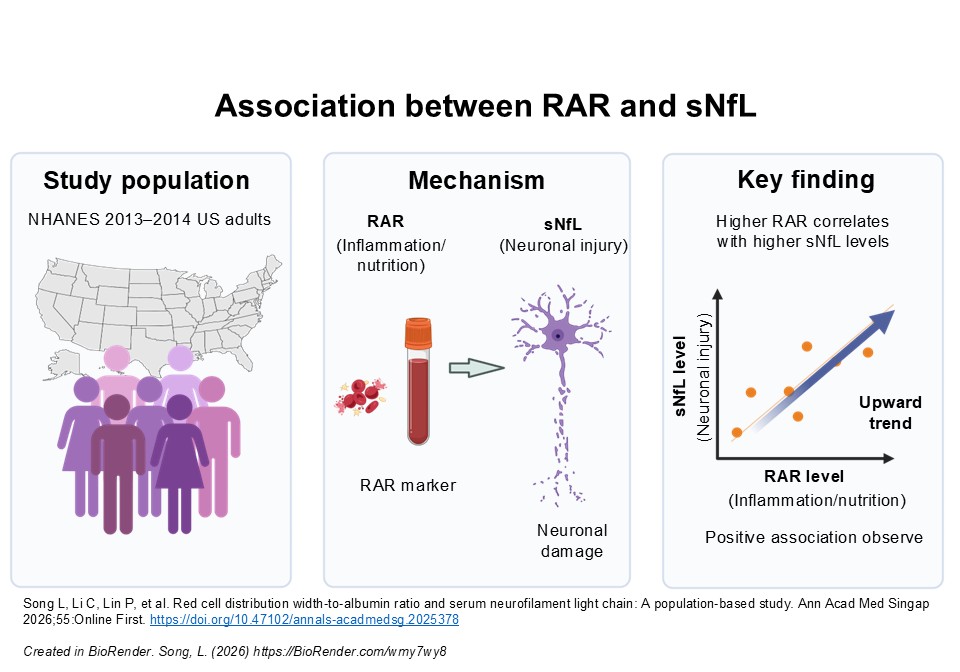
Introduction: Neurofilament light chain (NfL) is a blood biomarker of neuronal injury in inflammatory and neurodegenerative disorders. The red cell distribution width-to-albumin ratio (RAR) reflects systemic inflammation and nutritional status. This study investigated whether higher RAR is associated with higher serum NfL (sNfL) in a general adult population.
Methods: Data from 1750 adults who participated in the 2013–2014 National Health and Nutrition Examination Survey were analysed. RAR was calculated as red cell distribution width (%) divided by serum albumin (g/dL). sNfL was measured using an automated Atellica chemiluminescent immunoassay. Participants were grouped into RAR quartiles. Survey-weighted multivariable linear regression and restricted cubic spline (RCS) models assessed associations between RAR and log-transformed sNfL, adjusting for demographic, socioeconomic, lifestyle and clinical factors.
Results: Each unit increase in RAR was associated with higher sNfL in unadjusted analysis, and this association remained significant in partially and fully adjusted models. Compared with participants in the lowest quartile, those in the highest RAR quartile had higher sNfL, with a significant trend across quartiles. RCS analysis showed a non-linear but monotonic increase in log-transformed sNfL with higher RAR (P for non-linearity = 0.020). Associations varied by race/ethnicity, body mass index and diabetes status.
Conclusion: Higher RAR is associated with higher sNfL in US adults. This epidemiological association suggests that inflammation/nutritional status may relate to neuroaxonal injury. Longitudinal studies are needed to establish temporality and assess prognostic value before any clinical application.
CLINICAL IMPACT
What is New
- Analysis of 1750 US adults shows that higher red cell distribution width-to-albumin ratio (RAR) is associated with higher serum neurofilament light chain (sNfL).
- RAR–sNfL associations persist after adjustment for demographic and clinical factors, with variation by race/ethnicity, body mass index and diabetes status.
Clinical Implications
- RAR is calculated from routine full blood count and albumin tests and may help identify individuals with higher sNfL levels. These data support further prospective evaluation of RAR as a simple adjunctive marker of neuronal injury in diverse clinical populations.
Neurofilament light chain (NfL), a member of the neurofilament protein family, is highly expressed in the axons of mature neurons, where it forms a fibrous network that constitutes a key component of the neuronal cytoskeleton.1 When neurons die or are injured, NfL is released in large amounts into the extracellular space and subsequently reaches the cerebrospinal fluid and peripheral blood.2 Owing to its high solubility and abundant expression, NfL has become a reliable subunit for neurofilament detection in body fluids.
In recent years, NfL has been established as an early biomarker for various neurological diseases, including Alzheimer’s disease,3 frontotemporal dementia,4 Parkinson’s disease,5 amyotrophic lateral sclerosis,6 multiple sclerosis7 and traumatic brain injury.8 Under optimal conditions, NfL is also used to monitor treatment responses. Currently, Quanterix’s single-molecule array technology (Simoa; Quanterix Corporation, Lexington, MA, US) is regarded as the gold standard for measuring serum NfL (sNfL) levels.9 Accurate and flexible monitoring of blood NfL levels plays a crucial role in disease staging, subtyping and differential diagnosis.
The red cell distribution width-to-albumin ratio (RAR) has emerged as a novel composite biomarker reflecting both inflammatory and nutritional status. Red cell distribution width (RDW), an indicator of heterogeneity in red blood cell volume, is a readily available laboratory parameter, with higher values indicating greater variability in red blood cell size.10 Previous studies have shown that RDW is closely associated with various chronic inflammatory conditions and oxidative stress.11 Albumin, the most abundant plasma protein, exerts multiple physiological functions, including anti-inflammatory, anticoagulant and antioxidant activities, as well as the maintenance of osmotic pressure.12 Abnormalities in RDW and albumin levels may partially reflect alterations in nutritional status, inflammation and oxidative stress.13 As an integrated index, RAR has shown prognostic relevance or strong associations with several inflammation- and ageing-related conditions; however, its relationship with biomarkers of neuronal injury remains unclear.
This study aimed to investigate the association between RAR and sNfL levels. Clinically, the measurement of blood NfL often requires specialised platforms such as Simoa, which is expensive and not yet widely incorporated into routine laboratory testing. While NfL is a potent marker of injury, understanding how it relates to routine physiological indices remains limited. Exploring correlations between routinely available blood biomarkers and sNfL may therefore help elucidate the biological relationship between systemic physiological states and subclinical neuronal injury. Using data from the National Health and Nutrition Examination Survey (NHANES), this study conducted a cross-sectional analysis to evaluate the association between RAR and sNfL in US adults.
METHODS
Study population
This study focused on data from the 2013–2014 NHANES cycle, as it contains complete information on sNfL. Fig. 1 shows that 10,175 individuals were initially included. Participants were excluded based on the following criteria: (1) age under 20 years (n=4466), (2) missing sNfL data (n=3653), (3) missing RAR data (n=3) and (4) incomplete or missing covariate information (n=234).
The final analyses included relevant covariates such as age, sex, body mass index (BMI), poverty income ratio (PIR), education level, race/ethnicity, smoking status, alcohol consumption and the presence of diabetes or hypertension.
Fig. 1. Flowchart of participant selection.
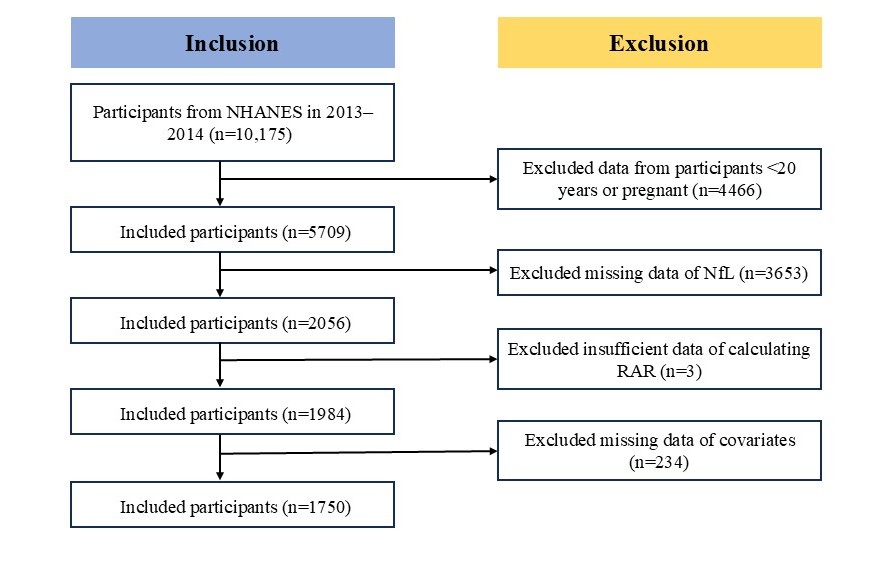 NHANES: National Health and Nutrition Examination Survey; NfL: neurofilament light chain; RAR: red cell distribution width-to-albumin ratio
Serum albumin concentrations were determined based on the formation of a coloured complex with bromocresol purple, where the colour intensity is directly proportional to the albumin level. The bichromatic digital endpoint method (DcX 800) was then used to measure absorbance and convert it into albumin concentration (g/dL).
Participants were divided into quartiles based on RAR values: Q1 (<2.95), Q2 (2.95–3.16), Q3 (3.16–3.44) and Q4 (>3.44), with Q1 defined as the reference group.
Measurement of NfL
In the 2013–2014 NHANES cycle, sNfL levels were measured using a highly sensitive chemiluminescent immunoassay developed by Siemens Healthineers. Serum samples were first incubated with acridinium ester (AE)-labelled antibodies specifically targeting NfL. Subsequently, paramagnetic microparticles (PMPs) were added to form a stable NfL–AE-labelled antibody–PMP complex.
After washing to remove unbound antibodies, a trigger solution was applied to initiate the chemiluminescent reaction of the AE label. The resulting light emission, which is directly proportional to the concentration of sNfL in the sample, was detected and quantified. All measurements were conducted using the Atellica IM analyzer platform (Siemens Healthineers, Tarrytown, NY, US), ensuring high-throughput processing and analytical consistency.
Covariates
Several covariates were included to account for demographic, lifestyle and clinical characteristics. Age was grouped as 20–39, 40–59 and ≥60 years; sex as male or female; and race/ethnicity as Mexican American, other Hispanic, non-Hispanic white, non-Hispanic black and other races. Educational attainment was categorised as less than high school, high school graduate or equivalent, and above high school. PIR was grouped as ≤1.3, 1.3–3.5 and >3.5. Marital status was classified as married or living with a partner, widowed/divorced/separated, or never married. Smoking status was defined according to whether participants had smoked at least 100 cigarettes in their lifetime. Alcohol consumption was defined as intake of more than 100 alcoholic drinks per year. Diabetes was identified by a clinical diagnosis or by any of the following: glycated haemoglobin ≥6.5%, fasting plasma glucose ≥7.0 mmol/L, random plasma glucose ≥11.1 mmol/L, 2-hour oral glucose tolerance test glucose ≥11.1 mmol/L, or use of glucose-lowering medication or insulin. Hypertension was defined as a clinical diagnosis or use of antihypertensive medication, or measured systolic/diastolic blood pressure ≥140/90 mmHg on 3 separate occasions by trained personnel. Laboratory covariates included total cholesterol (TC), uric acid (UA) and serum creatinine (Scr).
Statistical analyses
To better represent the US population, sample weights and stratified analyses were applied. As sNfL showed a non-normal distribution, its natural logarithm (ln) was used for analyses. Continuous variables are presented as mean ± standard deviation, and categorical variables as frequencies (percentages). The association between RAR and ln-transformed sNfL (ln-sNfL) was assessed using multivariable linear regression with 3 models: Model 1 (unadjusted), Model 2 (adjusted for age, sex, race/ethnicity, education, PIR and marital status) and Model 3 (further adjusted for smoking, alcohol use, diabetes, hypertension, TC, UA and Scr). A P-trend test evaluated potential trends. Restricted cubic spline (RCS) regression based on Model 2 examined possible non-linear associations. Subgroup and interaction analyses explored the relationship between RAR and ln-sNfL across categories of age, sex, race/ethnicity, education, PIR, marital status, BMI, smoking, alcohol use, diabetes and hypertension. All analyses were performed in R version 4.1.2 (R Foundation for Statistical Computing, Vienna, Austria), with 2-sided P<0.05 considered statistically significant.
RESULTS
Characteristics of the study population
Table 1 presents the baseline characteristics of 1750 eligible participants stratified by quartiles of RAR. Among them, 850 were male and 900 were female. Participants were categorised into 3 age groups in ascending order, and the proportion of individuals aged over 40 years gradually increased from the lowest (Q1) to the highest (Q4) RAR quartile. Compared with those in the low RAR group, participants with higher RAR were more likely to be female, non-Hispanic black and have lower income levels (P<0.05). Moreover, elevated RAR was more frequently observed in participants with obesity (BMI ≥30 kg/m²); smoking; alcohol consumption; hypertension; diabetes and higher levels of TC, UA and Scr, indicating that these unfavourable lifestyle factors and metabolic abnormalities tended to cluster in the higher RAR quartiles.
Table 1. Baseline characteristics of study participants in NHANES 2013–2014.
|
Variables |
Total |
RAR |
P |
|||
|
|
|
Q1 (≤2.95) |
Q2 (2.95–3.16) |
Q3 (3.16–3.44) |
Q4 (>3.44) |
|
|
n |
1750 |
439 |
442 |
433 |
436 |
|
|
Age, no. (%) |
|
|
|
|
|
|
|
20–39 |
609 (34.8) |
231 (52.6) |
158 (35.7) |
122 (28.2) |
98 (22.5) |
<0.001 |
|
40–59 |
674 (38.5) |
145 (33.0) |
169 (38.2) |
173 (40.0) |
187 (42.9) |
|
|
≥60 |
467 (26.7) |
63 (14.4) |
115 (26.0) |
138 (31.9) |
151 (34.6) |
|
|
Sex, no. (%) |
|
|
|
|
|
|
|
Male |
850 (48.6) |
285 (64.9) |
233 (52.7) |
188 (43.4) |
144 (33.0) |
<0.001 |
|
Female |
900 (51.4) |
154 (35.1) |
209 (47.3) |
245 (56.6) |
292 (67.0) |
|
|
Race, no. (%) |
|
|
|
|
|
|
|
Mexican American |
239 (13.7) |
59 (13.4) |
75 (17.0) |
50 (11.5) |
55 (12.6) |
<0.001 |
|
Other Hispanic |
154 (8.8) |
33 (7.5) |
45 (10.2) |
46 (10.6) |
30 (6.9) |
|
|
Non-Hispanic white |
811 (46.3) |
245 (55.8) |
210 (47.5) |
195 (45.0) |
161 (36.9) |
|
|
Non-Hispanic black |
309 (17.7) |
26 (5.9) |
41 (9.3) |
90 (20.8) |
152 (34.9) |
|
|
Other races (including multiracial) |
237 (13.5) |
76 (17.3) |
71 (16.1) |
52 (12.0) |
38 (8.7) |
|
|
Education, no. (%) |
|
|
|
|
|
|
|
Lower than high school |
348 (19.9) |
75 (17.1) |
76 (17.2) |
88 (20.3) |
109 (25.0) |
0.005 |
|
High school graduate/GED or equivalent |
367 (21.0) |
83 (18.9) |
87 (19.7) |
97 (22.4) |
100 (22.9) |
|
|
Higher than high school |
1035 (59.1) |
281 (64.0) |
279 (63.1) |
248 (57.3) |
227 (52.1) |
|
|
PIR, no. (%) |
|
|
|
|
|
|
|
≤1.3 |
597 (34.1) |
127 (28.9) |
138 (31.2) |
154 (35.6) |
178 (40.8) |
<0.001 |
|
1.3–3.5 |
589 (33.7) |
114 (26.0) |
164 (37.1) |
152 (35.1) |
159 (36.5) |
|
|
>3.5 |
564 (32.2) |
198 (45.1) |
140 (31.7) |
127 (29.3) |
99 (22.7) |
|
|
Marital status, no. (%) |
|
|
|
|
|
|
|
Married/living with partner |
1077 (61.5) |
275 (62.6) |
295 (66.7) |
255 (58.9) |
252 (57.8) |
<0.001 |
|
Widowed/divorced/separated |
333 (19.0) |
56 (12.8) |
68 (15.4) |
100 (23.1) |
109 (25.0) |
|
|
Never married |
340 (19.4) |
108 (24.6) |
79 (17.9) |
78 (18.0) |
75 (17.2) |
|
|
BMI, no. (%) |
|
|
|
|
|
|
|
<25 kg/m2 |
522 (29.8) |
185 (42.1) |
138 (31.2) |
127 (29.3) |
72 (16.5) |
<0.001 |
|
25–30 kg/m2 |
566 (32.3) |
160 (36.4) |
166 (37.6) |
137 (31.6) |
103 (23.6) |
|
|
≥30 kg/m2 |
662 (37.8) |
94 (21.4) |
138 (31.2) |
169 (39.0) |
261 (59.9) |
|
|
Smoking status, no. (%) |
|
|
|
|
|
|
|
Smokers |
778 (44.5) |
173 (39.4) |
199 (45.0) |
191 (44.1) |
215 (49.3) |
0.032 |
|
Non-smokers |
972 (55.5) |
266 (60.6) |
243 (55.0) |
242 (55.9) |
221 (50.7) |
|
|
Drinking status, no. (%) |
|
|
|
|
|
|
|
Drinkers |
1312 (75.0) |
356 (81.1) |
346 (78.3) |
316 (73.0) |
294 (67.4) |
<0.001 |
|
Non-drinkers |
438 (25.0) |
83 (18.9) |
96 (21.7) |
117 (27.0) |
142 (32.6) |
|
|
Diabetes, no. (%) |
|
|
|
|
|
|
|
Yes |
194 (11.1) |
21 (4.8) |
41 (9.3) |
48 (11.1) |
84 (19.3) |
<0.001 |
|
No |
1556 (88.9) |
418 (95.2) |
401 (90.7) |
385 (88.9) |
352 (80.7) |
|
|
Hypertension, no. (%) |
|
|
|
|
|
|
|
Yes |
621 (35.5) |
101 (23.0) |
132 (29.9) |
155 (35.8) |
233 (53.4) |
<0.001 |
|
No |
1129 (64.5) |
338 (77.0) |
310 (70.1) |
278 (64.2) |
203 (46.6) |
|
|
TC (mmol/L), mean (SD) |
189.02 (39.56) |
189.67 (39.81) |
193.10 (40.13) |
189.52 (38.27) |
183.75 (39.56) |
0.005 |
|
UA (mg/dL), mean (SD) |
5.47 (1.39) |
5.65 (1.37) |
5.39 (1.40) |
5.38 (1.37) |
5.46 (1.42) |
0.011 |
|
Scr (mg/dL), mean (SD) |
0.90 (0.63) |
0.88 (0.19) |
0.85 (0.19) |
0.86 (0.21) |
0.99 (1.21) |
0.002 |
|
NfL (pg/ml), mean (SD) |
2.56 (0.66) |
2.39 (0.57) |
2.53 (0.65) |
2.62 (0.63) |
2.70 (0.75) |
<0.001 |
BMI: body mass index; GED: general education development; NfL: neurofilament light chain; PIR: poverty income ratio; RAR: red cell distribution width-to-albumin ratio; Scr: serum creatinine; SD: standard deviation; TC: total cholesterol; UA: uric acid
The P value was calculated by weighted linear regression model.
Percentage for categorical variables: the P value was calculated by a weighted chi-square test.
Association between RAR and sNfL
Survey-weighted multivariable linear regression was conducted to examine the association between RAR and sNfL. Table 2 shows that higher RAR levels were significantly associated with increased ln-sNfL (β=0.23; 95% confidence interval [CI], 0.17–0.29; P<0.001). This association remained statistically significant after additional adjustment for demographic, socioeconomic, lifestyle and clinical factors in the fully adjusted model (β=0.14; 95% CI, 0.08–0.20; P<0.001). In sensitivity analyses, RAR was categorised into quartiles and treated as a categorical variable; the association persisted. Compared with individuals in the lowest quartile (Q1), those in the highest quartile (Q4) showed an adjusted β of 0.16 (95% CI, 0.08–0.25; P<0.001). Similar findings were observed in Models 1 and 2. Thus, higher RAR values were significantly associated with increased sNfL levels (P for trend <0.001). Additionally, RCS regression was used to assess the potential non-linear relationship between RAR and ln-sNfL. Fig. 2 illustrates that the test for non-linearity was statistically significant (P=0.02).
Table 2. Association of RAR with serum neurofilament light chain levels.
|
|
Model 1 |
Model 2 |
Model 3 |
|||
|
|
β (95% CI) |
P |
β (95% CI) |
P |
β (95% CI) |
P |
|
Continuous |
0.23 (0.17–0.29) |
<0.001 |
0.17 (0.11–0.23) |
<0.001 |
0.14 (0.08–0.20) |
<0.001 |
|
Q1 |
Reference |
Reference |
Reference |
|||
|
Q2 |
0.14 (0.05–0.23) |
0.001 |
0.07 (-0.01–0.14) |
0.087 |
0.07 (0.00–0.15) |
0.05 |
|
Q3 |
0.23 (0.15–0.32) |
<0.001 |
0.12 (0.04–0.20) |
0.003 |
0.13 (0.05–0.20) |
0.001 |
|
Q4 |
0.32 (0.23–0.40) |
<0.001 |
0.2 (0.12–0.28) |
<0.001 |
0.16 (0.08–0.25) |
<0.001 |
|
P for trend |
<0.001 |
|
<0.001 |
|
<0.001 |
|
CI: confidence interval; RAR: red cell distribution width-to-albumin ratio
Model 2 was adjusted for age, sex, race, education, poverty income ratio and marital status.
Model 3 was adjusted for age, sex, race, education, poverty income ratio, marital status, smoking status, drinking status, diabetes, hypertension, total cholesterol, uric acid and serum creatinine.
Fig. 2. RCS curve of the association between RAR and NfL.
 CI: confidence interval; NfL: neurofilament light chain; RAR: red cell distribution width-to-albumin ratio; RCS: restricted cubic spline
Stratified analyses
To further investigate how the association between RAR and sNfL varied across subgroups, stratified analyses were performed according to age, sex, race, education level, PIR, marital status and BMI (Table 3). The results indicated that the association between RAR and sNfL was significantly different across categories of race (P for interaction = 0.016), BMI (P for interaction <0.001) and diabetes status (P for interaction = 0.008), whereas no significant interactions were observed with other covariates. Across subgroups defined by age, sex, smoking status, alcohol consumption, diabetes and hypertension, RAR remained significantly positively associated with sNfL levels.
Table 3. Stratification analysis of the relationship between RAR and NfL based on Model 3.
|
Characteristics |
β (95% CI) |
P value |
P for interaction |
|
Age, no. (%) |
|
|
0.921 |
|
20–39 |
0.16 (0.04–0.27) |
0.008 |
|
|
40–59 |
0.14 (0.06–0.22) |
<0.001 |
|
|
≥60 |
0.12 (0.02–0.23) |
0.025 |
|
|
Sex, no. (%) |
|
|
0.146 |
|
Male |
0.20 (0.10–0.30) |
<0.001 |
|
|
Female |
0.11 (0.04–0.18) |
0.002 |
|
|
Race, no. (%) |
|
|
0.016a |
|
Mexican American |
0.10 (-0.05–0.25) |
0.175 |
|
|
Other Hispanic |
0.03 (-0.17–0.23) |
0.762 |
|
|
Non-Hispanic white |
0.20 (0.11–0.29) |
<0.001 |
|
|
Non-Hispanic black |
0.04 (-0.07–0.14) |
0.495 |
|
|
Other races (including multiracial) |
0.34 (0.16–0.53) |
<0.001 |
|
|
Education, no. (%) |
|
|
0.478 |
|
Lower than high school |
0.10 (-0.01–0.21) |
0.068 |
|
|
High school graduate/GED or equivalent |
0.12 (0.00–0.24) |
0.046 |
|
|
Higher than high school |
0.17 (0.09–0.25) |
<0.001 |
|
|
PIR, no. (%) |
|
|
0.096 |
|
≤1.3 |
0.20 (0.12–0.29) |
<0.001 |
|
|
1.3–3.5 |
0.10 (-0.00–0.20) |
0.056 |
|
|
>3.5 |
0.07 (-0.04–0.18) |
0.231 |
|
|
Marital status, no. (%) |
|
|
0.26 |
|
Married/living with partner |
0.11 (0.03–0.19) |
0.006 |
|
|
Widowed/divorced/separated |
0.21 (0.11–0.32) |
<0.001 |
|
|
Never married |
0.11 (-0.02–0.25) |
0.095 |
|
|
BMI, no. (%) |
|
|
<0.001a |
|
<25 kg/m2 |
0.16 (0.05–0.28) |
0.005 |
|
|
25–30 kg/m2 |
0.30 (0.19–0.41) |
<0.001 |
|
|
≥30 kg/m2 |
0.04 (-0.04–0.13) |
0.298 |
|
|
Smoking status, no. (%) |
|
|
0.371 |
|
Smokers |
0.16 (0.08–0.25) |
<0.001 |
|
|
Non-smokers |
0.12 (0.03–0.20) |
0.005 |
|
|
Drinking status, no. (%) |
|
|
0.197 |
|
Drinkers |
0.12 (0.05–0.19) |
<0.001 |
|
|
Non-drinkers |
0.20 (0.09–0.31) |
<0.001 |
|
|
Diabetes, no. (%) |
|
|
0.008a |
|
Yes |
0.34 (0.18–0.49) |
<0.001 |
|
|
No |
0.11 (0.05–0.18) |
<0.001 |
|
|
Hypertension, no. (%) |
|
|
0.389 |
|
Yes |
0.12 (0.04–0.20) |
0.005 |
|
|
No |
0.17 (0.08–0.25) |
<0.001 |
|
BMI: body mass index; CI: confidence interval; GED: general education development; NfL: neurofilament light chain; PIR: poverty income ratio; RAR: red cell distribution width-to-albumin ratio
a statistically significant
DISCUSSION
To the authors’ knowledge, this study is the first cross-sectional analysis based on data from the nationally representative NHANES 2013–2014 cohort. Data from 1750 participants were analysed to investigate the association between RAR and sNfL. Results from multivariable linear regression (Model 3), which adjusted for multiple covariates, demonstrated a significant positive relationship between RAR and sNfL (both raw and log-transformed values, ln-sNfL), showing that higher RAR levels are associated with higher levels of a blood biomarker of neuronal injury. The findings, supported by stratified linear models and RCS analyses, suggested a monotonic increasing association without an obvious threshold. Interaction analyses revealed that race, BMI and diabetes status were significant effect modifiers of the association between RAR and sNfL. Overall, these results provide epidemiological evidence linking a composite marker of systemic inflammation and nutritional status with a blood biomarker of neuroaxonal injury.
sNfL is recognised as a sensitive biomarker of axonal damage and has shown considerable clinical and research utility in various neurological disorders. Recent studies have demonstrated that sNfL levels are elevated in patients with multiple sclerosis,14 depression,15 cognitive impairment16 and cerebrovascular diseases.17 Accordingly, sNfL is widely utilised in research and clinical settings to reflect the burden of neuro-axonal damage, as well as for prognostic evaluation and monitoring disease progression in these conditions.18 However, sNfL is not disease-specific and may reflect neuroaxonal injury arising from multiple neurological and systemic processes. Thus, these findings should be interpreted as an epidemiological association rather than evidence supporting a specific clinical diagnostic or screening application.
The ratio of RAR has recently been proposed as a comprehensive indicator reflecting inflammation and nutritional metabolism.19 Calculated from RDW and serum albumin, RAR combines these 2 parameters to more comprehensively reflect inflammatory status, oxidative stress and nutritional imbalance, and may provide more prognostic information than RDW or albumin alone.13 Elevated RAR is associated with adverse systemic inflammatory and wasting diseases, such as sepsis, cancer and heart failure.20-23 Moreover, recent research has revealed a positive correlation between high RAR levels and the prevalence of kidney stones in adults.24 Increased RAR has also been linked to higher mortality risk in the general population,13 and rising RAR levels may serve as a potential predictive marker for depression.25
While these findings support the positive association between RAR and sNfL, the underlying mechanisms remain speculative. RDW, the main component of RAR, reflects variability in red blood cell volume (anisocytosis) and is often associated with nutritional deficiencies, chronic inflammation and other pathological conditions.26 Prior studies suggest that changes in RDW and related haematological parameters may be linked to neural vulnerability, although the biological pathways connecting RDW, albumin and neuroaxonal injury remain unclear. Albumin, a major extracellular protein, contributes to plasma oncotic pressure, transport functions, microcirculatory regulation and antioxidant/anti-inflammatory capacity,12,27 which may be relevant to systemic and vascular homeostasis. Epidemiological studies have reported associations between lower albumin levels and higher risk of neural injury; however, direct experimental evidence supporting a causal role of albumin deficiency in neurodegeneration remains limited. This study does not directly address these mechanisms. Further research is needed to clarify how RAR may relate to neuroaxonal damage, particularly in the context of inflammatory and nutritional imbalances.
Overall, our findings highlight the potential clinical utility of RAR as a readily accessible indicator for evaluating the risk of neuronal injury. Determining its specific prognostic and risk-stratification value will be an important direction for future clinical research.
CONCLUSION
This cross-sectional study, based on data from NHANES, demonstrated a significant positive association between RAR and sNfL in US adults. These findings suggest a potential link between systemic inflammation, nutritional status and blood biomarkers of neuronal injury. However, given the nature of the study, further large-scale, multicentre prospective studies are necessary to validate these associations, establish temporal relationships and explore the underlying biological mechanisms linking RAR, systemic inflammation, nutritional status and neural injury.
REFERENCES
- Abu-Rumeileh S, Abdelhak A, Foschi M, et al. The multifaceted role of neurofilament light chain protein in non-primary neurological diseases. Brain 2023;146:421-37.
- Gaetani L, Blennow K, Calabresi P, et al. Neurofilament light chain as a biomarker in neurological disorders. J Neurol Neurosurg Psychiatry 2019;90:870-81.
- Shim Y. Clinical Application of Plasma Neurofilament Light Chain in a Memory Clinic: A Pilot Study. Dement Neurocogn Disord 2022;21:59-70.
- Karantali E, Kazis D, Chatzikonstantinou S, et al. The role of neurofilament light chain in frontotemporal dementia: a meta-analysis. Aging Clin Exp Res 2021;33:869-81.
- Buhmann C, Magnus T, Choe CU. Blood neurofilament light chain in Parkinson’s disease. J Neural Transm (Vienna) 2023;130:755-62.
- Sugimoto K, Han Y, Song Y, et al. Correlational Analysis of ALS Progression and Serum NfL Measured by Simoa Assay in Chinese Patients. Front Neurol 2020;11:579094.
- Freedman MS, Gnanapavan S, Booth RA, et al. Guidance for use of neurofilament light chain as a cerebrospinal fluid and blood biomarker in multiple sclerosis management. EBioMedicine 2024;101:104970.
- Guedes VA, Kenney K, Shahim P, et al. Exosomal neurofilament light: A prognostic biomarker for remote symptoms after mild traumatic brain injury? Neurology 2020;94:e2412-23.
- Altmann P, Leutmezer F, Zach H, et al. Serum neurofilament light chain withstands delayed freezing and repeated thawing. Sci Rep 2020;10:19982.
- Parizadeh SM, Jafarzadeh-Esfehani R, Bahreyni A, et al. The diagnostic and prognostic value of red cell distribution width in cardiovascular disease; current status and prospective. Biofactors 2019;45:507-16.
- García-Escobar A, Lázaro-García R, Goicolea-Ruigómez J, et al. Red Blood Cell Distribution Width is a Biomarker of Red Cell Dysfunction Associated with High Systemic Inflammation and a Prognostic Marker in Heart Failure and Cardiovascular Disease: A Potential Predictor of Atrial Fibrillation Recurrence. High Blood Press Cardiovasc Prev 2024;31:437-49.
- Abedi F, Zarei B, Elyasi S. Albumin: a comprehensive review and practical guideline for clinical use. Eur J Clin Pharmacol 2024;80:1151-69.
- Hao M, Jiang S, Tang J, et al. Ratio of Red Blood Cell Distribution Width to Albumin Level and Risk of Mortality. JAMA Netw Open 2024;7:e2413213.
- Siddiqui K, Browne RW, Benedict RHB, et al. Cholesterol pathway biomarkers are associated with neuropsychological measures in multiple sclerosis. Mult Scler Relat Disord 2023;69:104374.
- Habibzadeh A, Ostovan VR, Ghezel MA, et al. Neurofilament light chain as a promising biomarker for depression diagnosis: a systematic review and meta-analysis. BMC Psychiatry 2024;24:617.
- Yao W, Zhou H, Zhang X, et al. Inflammation affects dynamic functional network connectivity pattern changes via plasma NFL in cognitive impairment patients. CNS Neurosci Ther 2024;30:e14391.
- Gundersen JK, Gonzalez-Ortiz F, Karikari T, et al. Neuronal plasma biomarkers in acute ischemic stroke. J Cereb Blood Flow Metab 2025;45:77-84.
- Thebault S, Booth RA, Freedman MS. Blood Neurofilament Light Chain: The Neurologist’s Troponin? Biomedicines 2020;8:523.
- Seo YJ, Yu J, Park JY, et al. Red cell distribution width/albumin ratio and 90-day mortality after burn surgery. Burns Trauma 2022;10:tkab050.
- Xu W, Huo J, Chen G, et al. Association between red blood cell distribution width to albumin ratio and prognosis of patients with sepsis: A retrospective cohort study. Front Nutr 2022;9:1019502.
- Lu C, Long J, Liu H, et al. Red blood cell distribution width-to-albumin ratio is associated with all-cause mortality in cancer patients. J Clin Lab Anal 2022;36:e24423.
- Zhou P, Tian PC, Zhai M, et al. Association between red blood cell distribution width-to-albumin ratio and prognosis in non-ischaemic heart failure. ESC Heart Fail 2024;11:1110-20.
- Guo H, Wang Y, Miao Y, et al. Red cell distribution width/albumin ratio as a marker for metabolic syndrome: findings from a cross-sectional study. BMC Endocr Disord 2024;24:227.
- Wu L, Zhang Y, Chen D, et al. Association of Red Blood Cell Distribution Width to Albumin Ratio With the Prevalence of Kidney Stones Among the General Adult Population. Immun Inflamm Dis 2024;12:e70070.
- Zhou Y, Zhao L, Tang Y, et al. Association between red blood cell distribution width-to-albumin ratio and depression: a cross-sectional analysis among US adults, 2011–2018. BMC Psychiatry 2025;25:464.
- Salvagno GL, Sanchis-Gomar F, Picanza A, et al. Red blood cell distribution width: A simple parameter with multiple clinical applications. Crit Rev Clin Lab Sci 2015;52:86-105.
- Prajapati KD, Sharma SS, Roy N. Current perspectives on potential role of albumin in neuroprotection. Rev Neurosci 2011;22:355-63.
The data used in this study were obtained from the publicly available NHANES database (https://www.cdc.gov/nchs/nhanes/index.htm). All NHANES protocols were approved by the National Center for Health Statistics Ethics Review Board, and written informed consent was obtained from all participants.
This study was supported by the National Natural Science Foundation of China (82201578 and 82401691) and the China Postdoctoral Foundation (2025M782403). The authors declare that there are no affiliations with or involvement in any organisation or entity with any financial interest in the subject matter or materials discussed in this manuscript. The authors also declare that they have no conflicts of interest. ChatGPT (OpenAI, San Francisco, CA, US) was used only for spelling and minor language corrections. All scientific content, analyses, and conclusions were generated and confirmed by the authors.
Dr Xiaojiao Xiang, Department of Nuclear Medicine, The Second Affiliated Hospital of Chongqing Medical University, Chongqing, China 400010. Email: [email protected]; Dr Jianshuang Liu, Department of Obstetrics and Gynecology, Women and Children’s Hospital of Chongqing Medical University (Chongqing Health Center for Women and Children), Chongqing, China. Email: [email protected]
